

Precision Postoperative Rehabilitation Case of Colorectal Cancer
Introduction
This case focuses on Mr. Chen, a patient in the postoperative recovery period after colorectal cancer surgery. Although the surgery has been completed, he still faces dual high risks: bilateral carotid atherosclerotic plaques, with the right side being a hypoechoic vulnerable plaque at high risk of rupture; tumor marker CA72-4 is significantly elevated, suggesting potential recurrence or a persistent high-risk internal environment.
Although conventional treatment can partially control the indicators, it is difficult to reverse the adverse internal environment of "chronic systemic inflammation + high-risk vascular plaques."
Based on functional medicine assessment and Dr. Bob Miller FGA full functional genomic testing, we identified key genetic susceptibilities in his antioxidant, autophagy, inflammatory-immune, and methylation pathways, and implemented a closed-loop intervention of "5R gut repair + gene-guided precision nutrition."
After 14 months of precision intervention, encouraging results were achieved: not only was CA72-4 significantly reduced, but follow-up imaging also witnessed the complete disappearance of the vulnerable carotid plaque, suggesting that elevating postoperative colorectal cancer management to a precision functional medicine model at the "gut–gene–vascular axis" level may provide a new integrated pathway for tumor rehabilitation and cardiovascular reversal.
Basic Information
Name:Mr. Chen
Gender:Male
Age:58 years old
Medical History:Postoperative recovery period after colorectal cancer surgery
Core needs:
1. Management of bilateral carotid atherosclerotic plaques, especially stroke risk control of vulnerable plaques
2. Functional medicine intervention for abnormal tumor markers
I. Initial Diagnosis and Functional Medicine Diagnosis
1. Laboratory: Tumor Markers Suggest a "Chronic Mucosal Inflammation Storm"
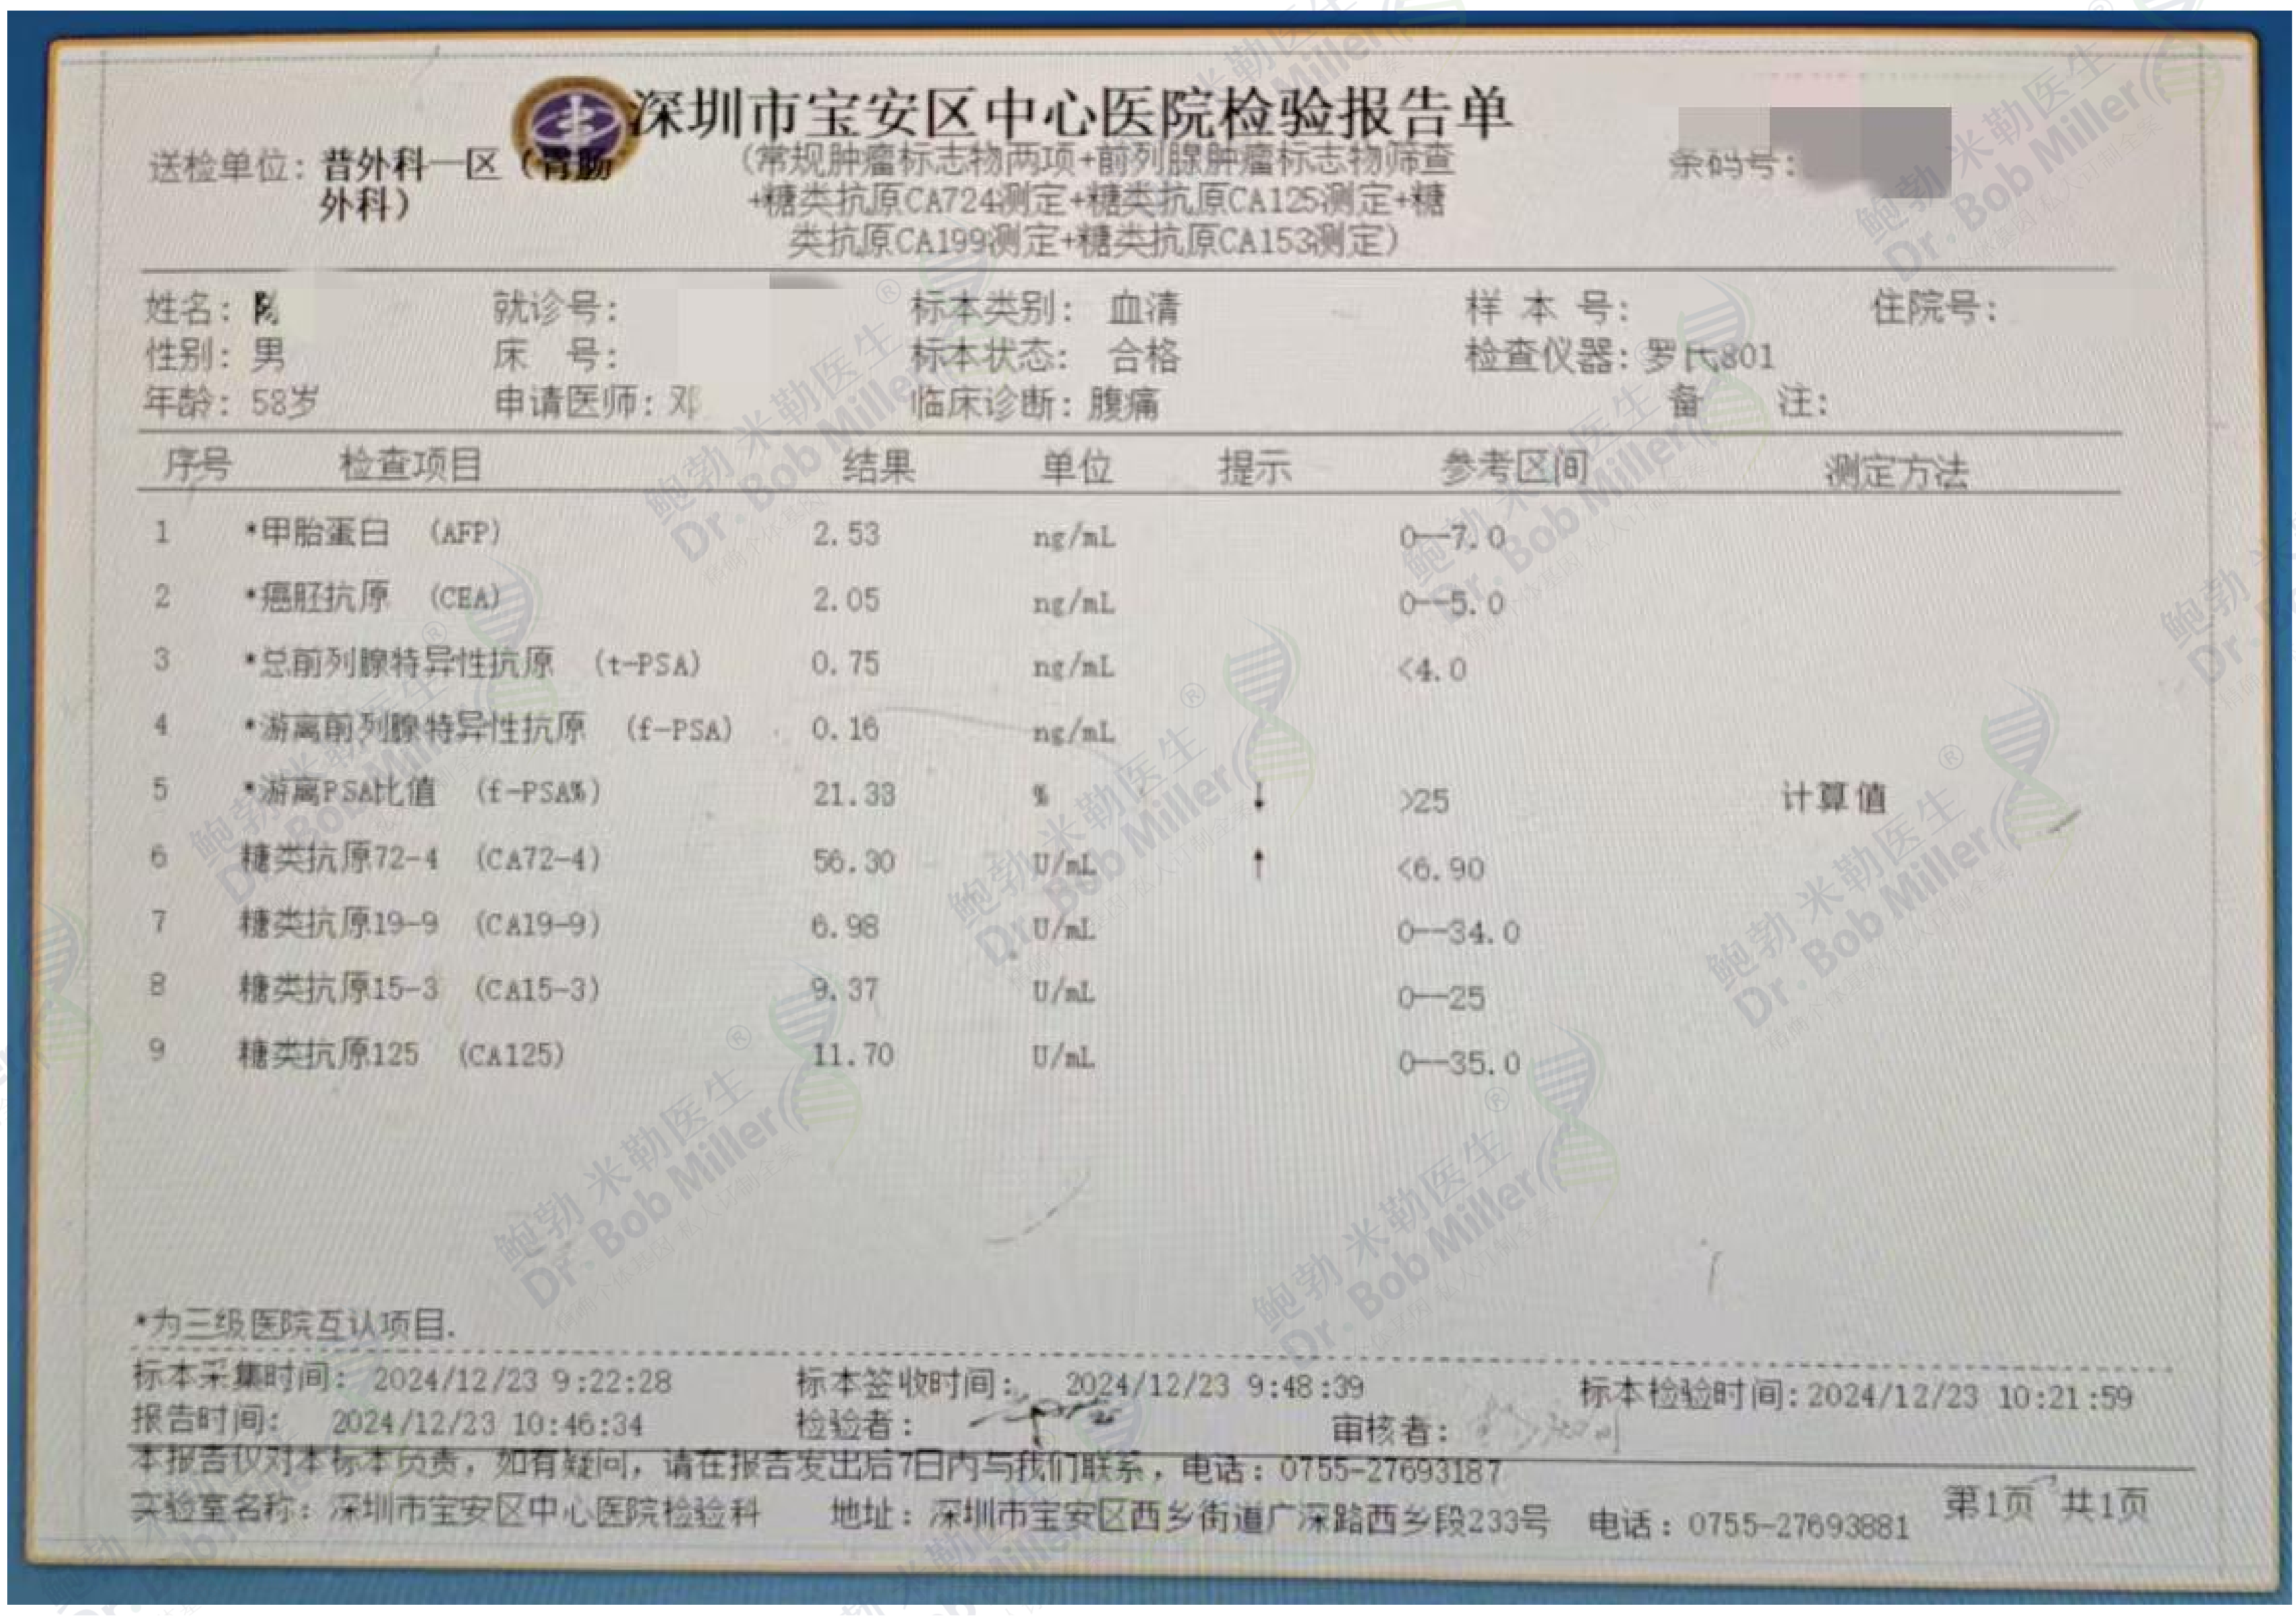
CA72-4 at initial diagnosis: 56.30 U/mL (significantly elevated; reference value <6.90 U/mL)
Functional medicine interpretation:For patients after colorectal cancer surgery, CA72-4 is not only a marker for monitoring tumor recurrence, but also an important indicator reflecting the integrity of the gastrointestinal mucosal barrier, chronic inflammation level, and immune activation status.
This patient's persistently significantly elevated CA72-4 suggests: impaired intestinal barrier function, high intestinal and systemic inflammatory activity, and dual risk signals for tumor recurrence and metabolic syndrome.
2. Imaging: Typical High-Risk "Vulnerable Plaque" Phenotype

Bilateral carotid intima-media thickness (IMT) was increased; a 15.2×3.4 mm hypoechoic plaque was seen at the right carotid bifurcation.
Risk assessment:Hypoechoic plaques often indicate lipid-rich content, thin fibrous cap, and active inflammation, belonging to vulnerable plaques; this is highly associated with high stroke risk, and stabilization alone is insufficient to meet the patient's needs.
3. Dr. Bob Miller Functional Genomics: Identifying Metabolic Bottlenecks
Through FGA functional genetic testing, important SNP variants were found in the following five pathways, forming the patient's disease baseline of "congenital susceptibility + acquired environmental triggers."
① Antioxidant Pathway Deficiency (SOD2/GPX/NRF2-related)
Reduced efficiency of the superoxide dismutase and glutathione peroxidase systems.
Results:Inefficient peroxide clearance leaves the vascular endothelium chronically exposed to oxidative stress and peroxynitrite (ONOO⁻) attacks; the inflammatory-immune pathway is easily activated (TNF-α/IL-6/NF-κB).
② Easy Activation of Inflammatory-Immune Pathways (TNF-α/IL-6/NF-κB-related)
Genetic polymorphisms of pro-inflammatory cytokines enhance NF-κB signaling sensitivity.
Results:NF-κB is more easily activated and harder to stop, sustaining chronic low-grade inflammation, promoting endothelial dysfunction, accelerating atherosclerosis, and driving inflammation in the tumor microenvironment.
③ Autophagy and Scavenger System Deficiency (RPTOR/NRF2-related)
Reduced efficiency of autophagy initiation and lysosomal clearance impairs the vascular wall's waste-removal function.
Results:Damaged proteins and oxidized LDL are difficult to degrade promptly; foam cells continue to accumulate within the vessel wall, the necrotic core within the plaque expands, the fibrous cap becomes thinner, and the plaque becomes more prone to rupture.
④ Mitochondrial and Energy Metabolism Limitation (NADSYN1/PARP-related)
NAD+ synthesis and the activity of DNA damage repair-related enzymes are limited.
Results:Mitochondria produce insufficient energy and ATP supply declines; endothelial cells "work while impaired," repair cannot keep pace with injury, microcirculatory perfusion decreases, and the risk of tissue ischemia-reperfusion injury increases.
⑤ Methylation and Homocysteine Pathway Dysfunction (MTHFR/MTR-related)
One-carbon metabolism and the methyl donor cycle are impaired.
Results:Abnormal DNA and RNA methylation affects cell proliferation and repair programs; homocysteine (Hcy) clearance slows, plasma Hcy tends to rise, increasing cardiovascular events risk and the possibility of recurrence and metastasis after colorectal cancer surgery.
II. Intervention Strategy: Precision Targets + Closed Loop of the Gut–Gene–Vascular Axis
Overall goal:Turn off the source of inflammation (gut + NF-κB); restore autophagy and scavenger function to promote plaque regression; fiber network intervention (gentle dissolution); stabilize the fibrous cap (prevent plaque detachment); bypass genetic defects for nutritional reprogramming (antioxidant + methylation); maintain a long-term low-inflammation environment, balancing cardiovascular and tumor risks.
1. Anti-inflammatory and Metabolic Reconstruction of the Vascular Endothelium
Key ingredients:Longvida® curcumin, ParActin® andrographolide, and boswellia extract
Mechanism highlights:Blocking NF-κB from entering the nucleus, reducing inflammatory cytokines such as TNF-α and IL-6; downregulating endothelial adhesion molecules and reducing monocyte adhesion/infiltration, providing a low-inflammation environment for plaque reversal.
2. Autophagy and Senescent Cell Clearance: The Engine of Plaque Reversal
Key ingredients:Spermidine, Fisetin 98%, Apigenin 98%
Spermidine: activates autophagy, promotes clearance of damaged mitochondria, oxidized LDL, and cellular debris, and reduces the lipid necrotic core.
Fisetin + Apigenin: as gentle senolytic agents, they induce apoptosis of "zombie cells" and reduce plaque inflammation.
Expected result:Once inflammation is suppressed, the plaque is not only stabilized but gradually reversed and eliminated.
3. Fiber Network Intervention (Gentle Dissolution): A "Dismantling Tool" for Thrombus/Fibrin Networks
Key ingredients:Lumbrokinase, serrapeptase, and bromelain
Lumbrokinase: activates the fibrinolytic system, breaks down fibrin, gently clears thrombus-like deposits, and reduces blood flow resistance.
Serrapeptase: degrades inflammation-related proteins and fibrin deposits, reduces fibrosis and adhesion around plaques, and facilitates plaque remodeling and absorption.
Bromelain: gently hydrolyzes proteins and provides anti-inflammatory effects, helping break down small fibrin clumps and inflammatory exudates, reduce blood viscosity, and improve microcirculation.
4. Fibrous Cap Stabilization (Preventing Plaque Rupture)
Key ingredients:Centella asiatica extract strongly promotes collagen synthesis in the vessel wall and reinforces the fibrous cap.
5. Bypass Support for Antioxidation and Methylation
Key ingredients:S-acetyl glutathione, Quatrefolic® active folate, NR, and PQQ
GSH: bypasses SOD2 limitations, directly enhances cellular reducing power, and reduces ONOO⁻ damage to endothelial cells/mitochondria.
Quatrefolic® active folate: bypasses MTHFR/MTR defects, improving DNA methylation and homocysteine metabolism.
NR + PQQ: increase NAD+, promote mitochondrial biogenesis and repair, and accelerate endothelial repair and stress resistance.
6. Gut–Gene–Vascular Axis: Cutting Off Inflammation at the Source
Sections 1–3 above are precision interventions directly targeting vessels and cells. This section uses the 5R gut repair protocol to reduce the frequency of NF-κB activation at the source, providing a durable low-inflammation background for the above interventions and later plaque reversal.
Mechanistic link:Leaky gut → LPS enters the bloodstream → activates TLR4 → NF-κB → systemic endothelial inflammation. The 5R protocol repairs the barrier and microbiota, directly reducing LPS burden and creating a "low-inflammation, low-toxin" internal environment for subsequent autophagy and gene-nutrition interventions.
III. Treatment Verification: Miraculous Imaging and Biochemical Reversal!
After 14 months of precision intervention, the patient's follow-up results demonstrated remarkable clinical value:
1. Tumor Marker: CA72-4 Decreased Significantly by 63%
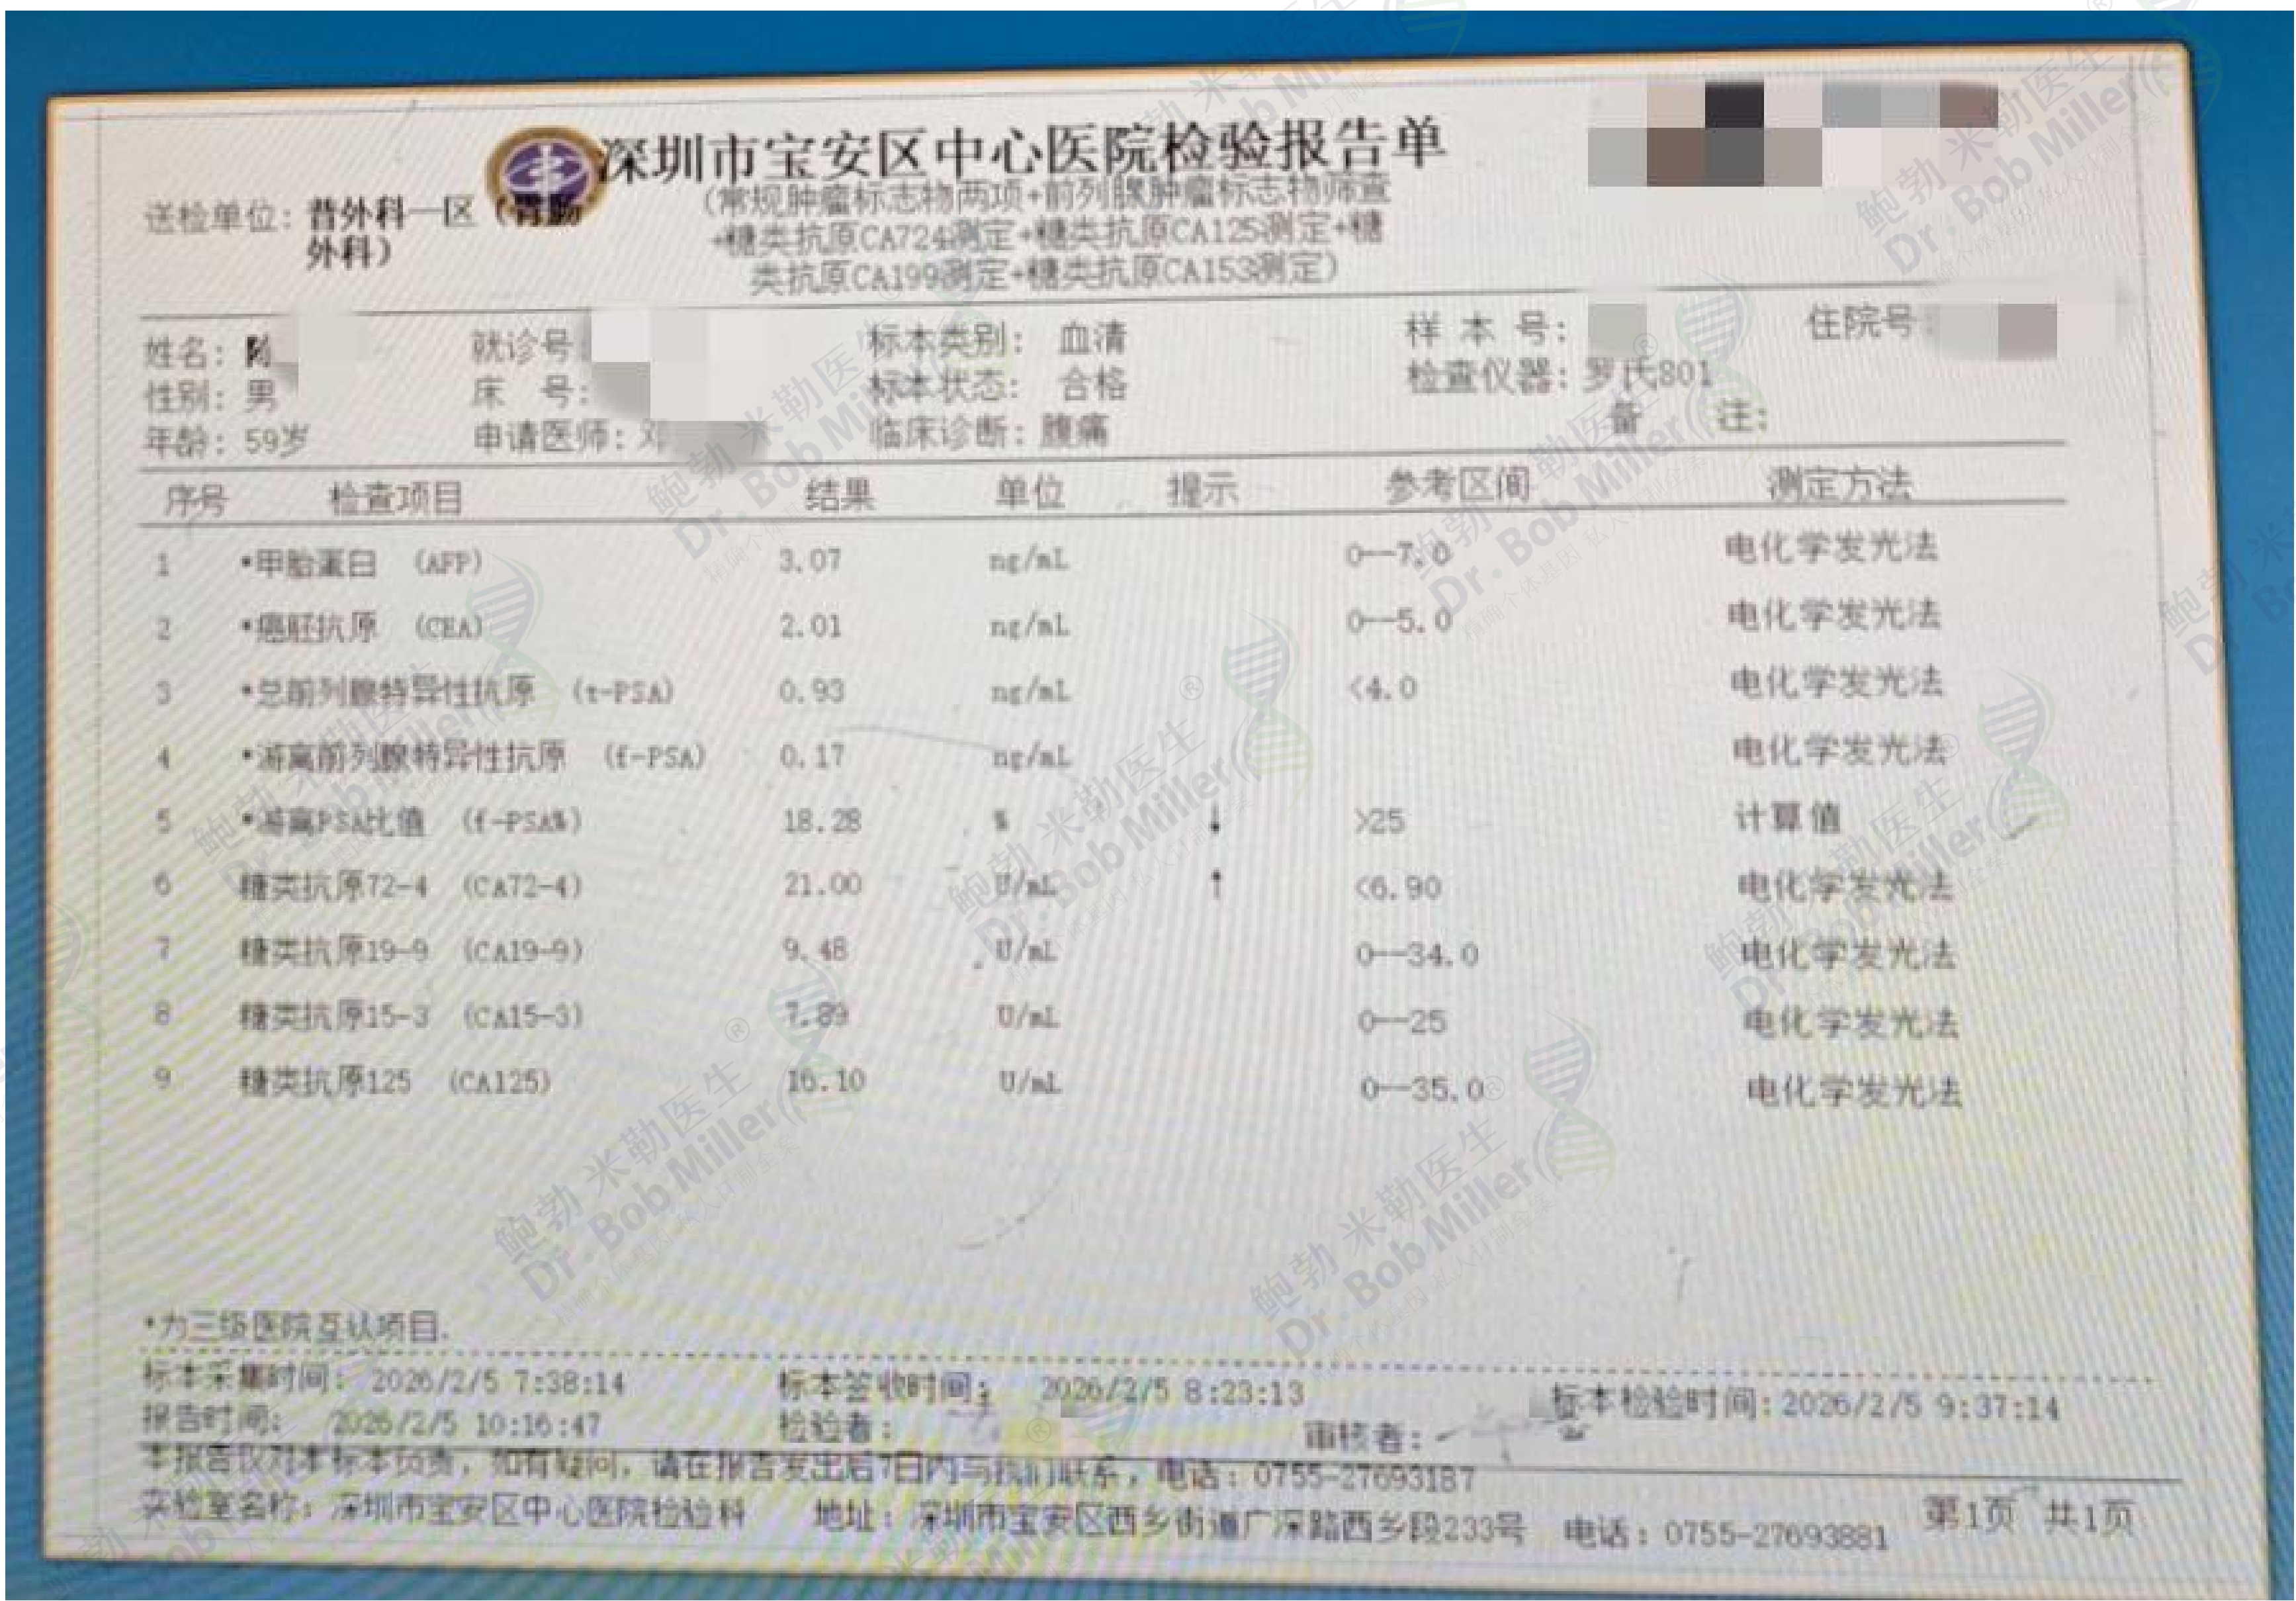
Initial diagnosis:56.30 U/mL → Follow-up:21.00 U/mL (↓63%)
Clinical implications:For postoperative colorectal cancer patients, such a decline: suggests significant alleviation of gastrointestinal mucosal inflammatory activity; supports the effectiveness of the 5R gut protocol + gene-nutrition intervention on the intestinal inflammation–tumor susceptibility axis; provides a safer biological window for subsequent long-term tumor follow-up.
2. Carotid Ultrasound: Bilateral Plaques "Disappeared" on Imaging
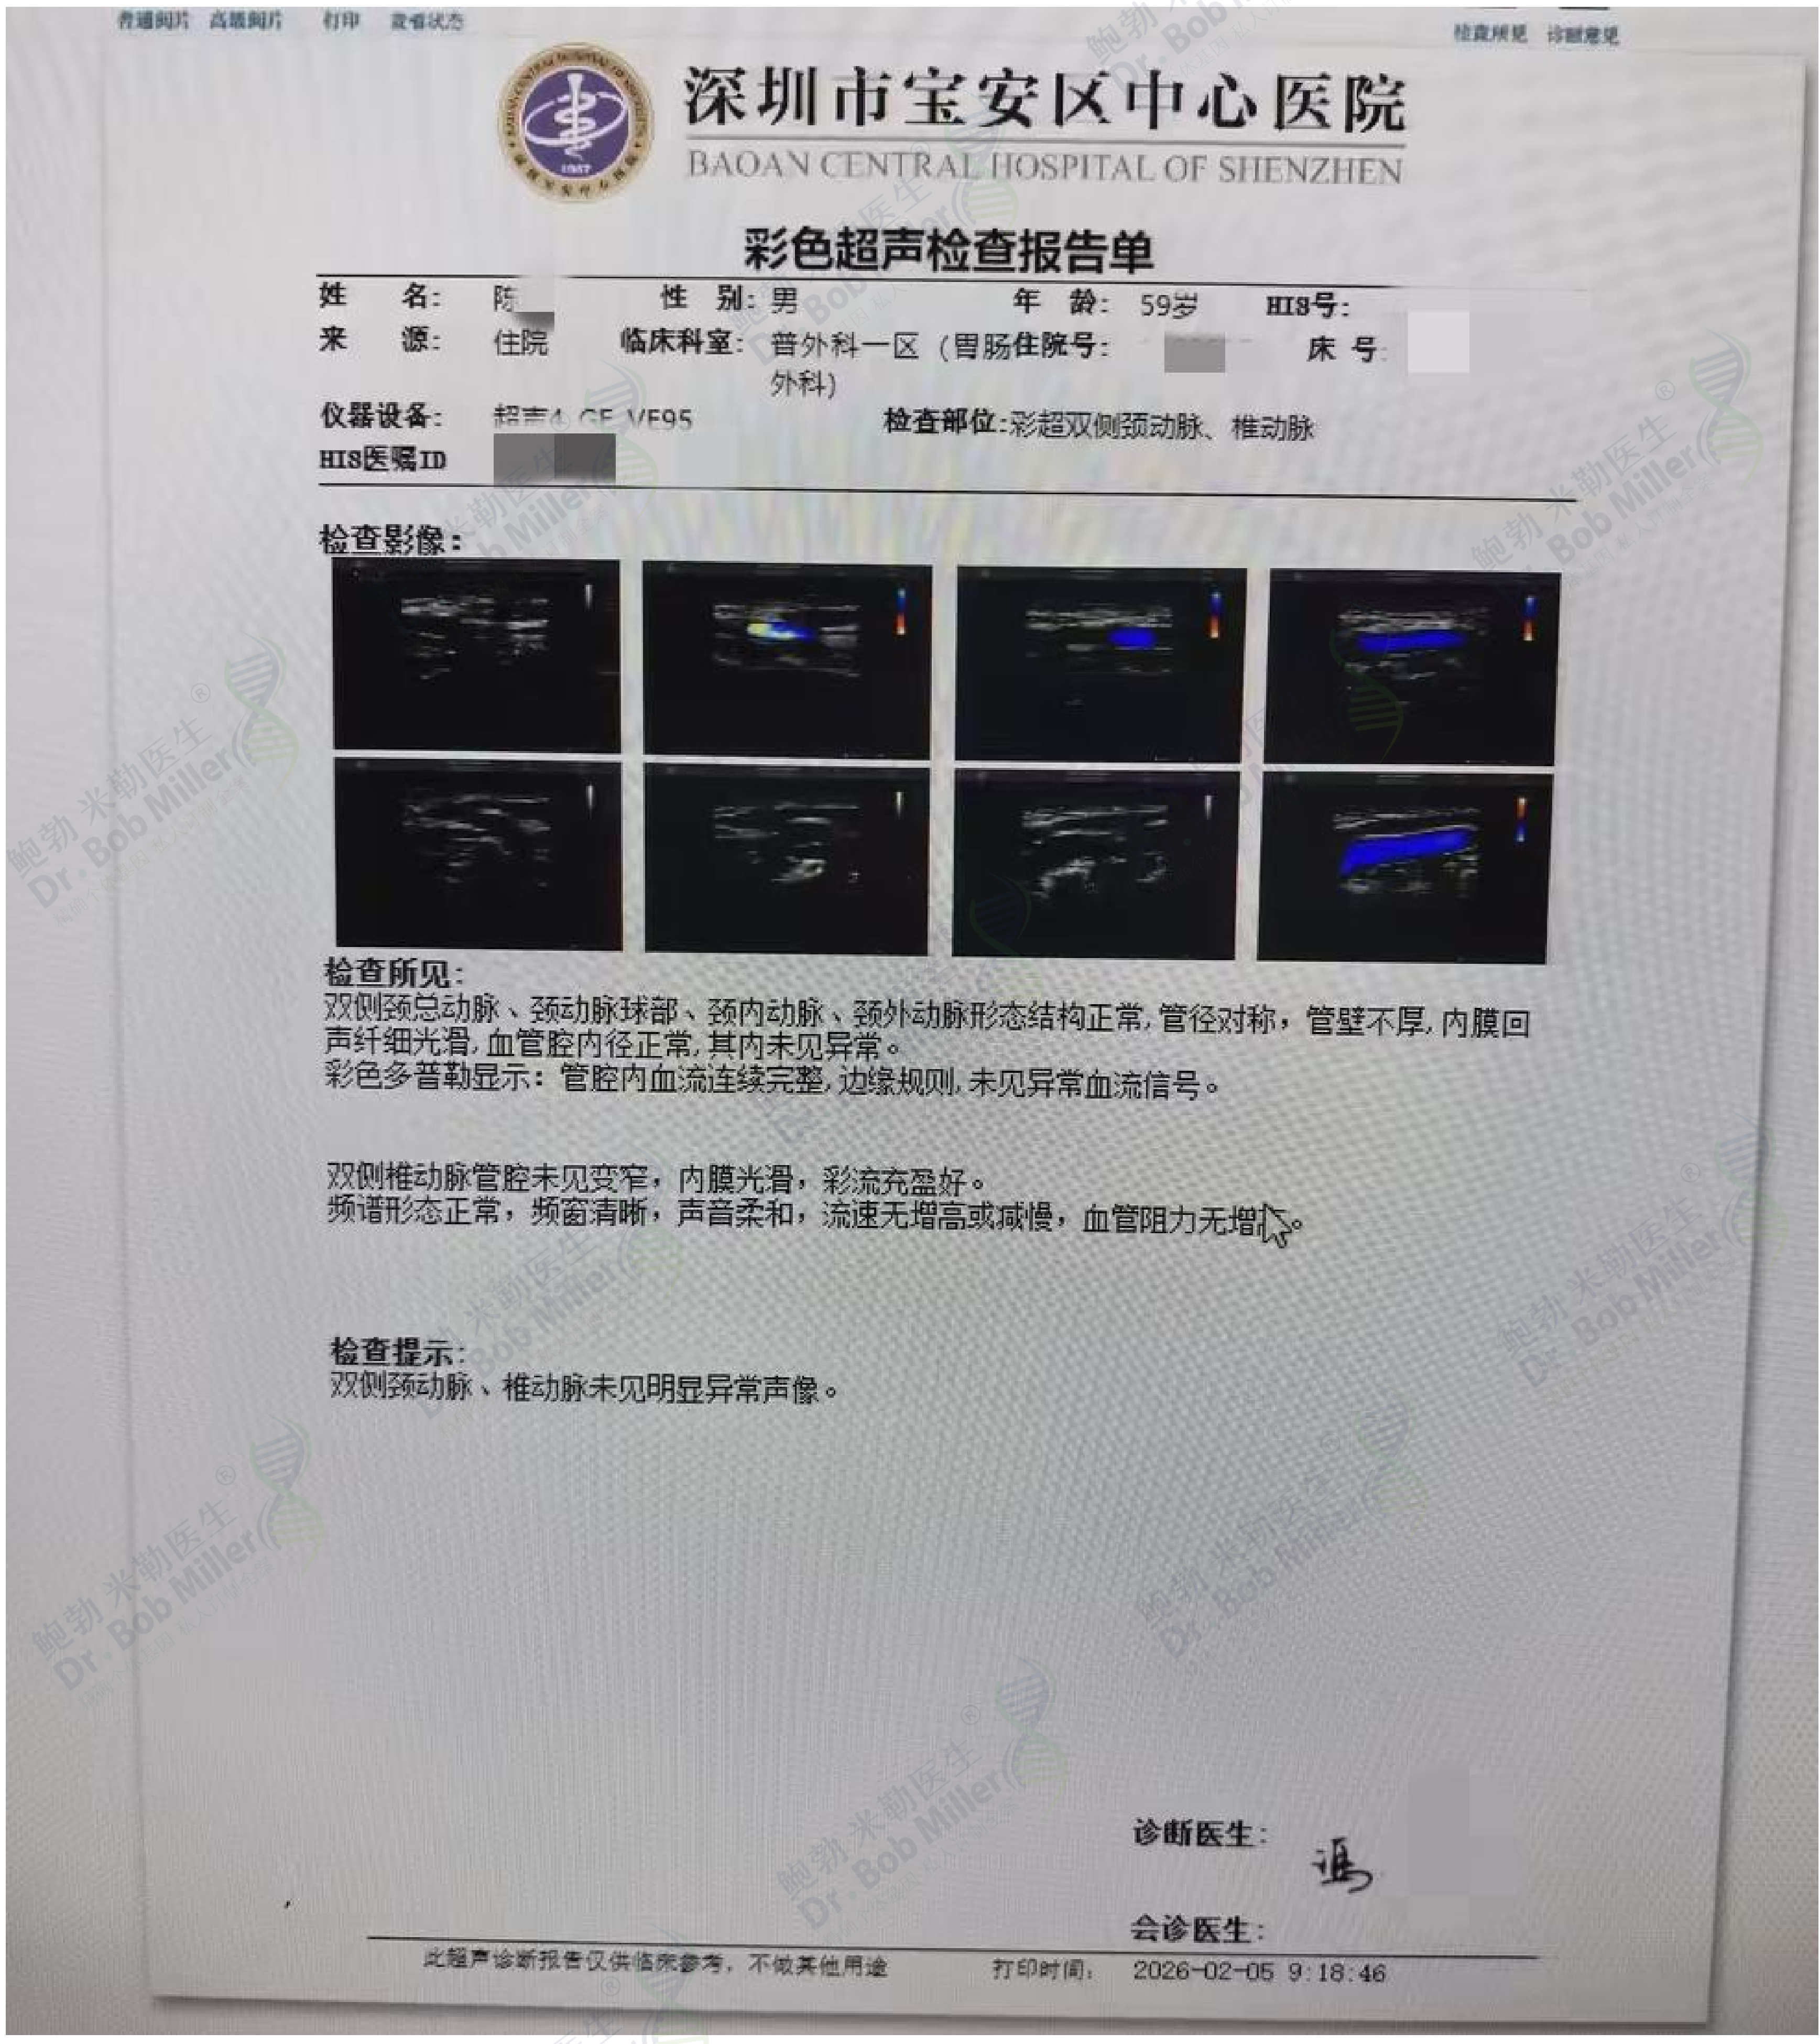
Initial diagnosis:Right carotid bifurcation: 15.2×3.4 mm hypoechoic vulnerable plaque.
Follow-up:Bilateral carotid walls were regular; blood flow within the lumen was continuous with no obvious abnormal echoes. The original plaques completely disappeared on imaging.
IV. Clinical Insights and Conclusions
1. Plaques Are Not Irreversible.Traditional thinking holds that plaques can only be stabilized with statins. However, in this case, by activating autophagy and clearing senescent cells, combined with precise nutritional support, the plaque can be physiologically dismantled and absorbed by the body, as confirmed by imaging.
2. Genes Are the Manual; the Gut Is the Engine.First use the 5R protocol to repair the gut and shut off the source of inflammation; then, based on Dr. Bob Miller FGA gene maps, provide targeted PN precision nutritional supplementation. Stabilize the engine first, then add precise parts according to the manual, so the therapeutic effect can be sustained and amplified.
3. The Key to Precision Medicine: Not More Supplements, but the Right Ones.Without considering the patient's genetic defects in antioxidant and autophagy pathways, conventional supplementation alone is unlikely to achieve this case's leap of significant CA72-4 reduction + complete imaging disappearance of carotid plaques. The value of precision nutrition lies in designing protocols by pathway, by gene, and by individual.
This case demonstrates a true precision medicine paradigm:Based on genetic and functional assessment; using Dr. Bob Miller PN precision nutrients as tools; designed by pathway and individualized; every nutrient has a clear mechanistic positioning and clinical expectation.



